Friday, November 6, 2020

Lupine Publishers | MDCT in Diagnosis of Anomalies of Coronary Artery Origin and Course a Coronary MDCT-Angiographic study of 9572 patients

   Lupine Publishers | Advancements in Cardiology Research & Reports


Abstract

Background: Coronary anomalies are the causes of sudden cardiac deaths in young peoples, but usually asymptomatic. We perform this retrospective study to determine the types and prevalence of Coronary Anomalies of origin and course.

Method: The data of 9572 patients with Coronary CT-angiography by MDCT 640 Aquilion Toshiba machine were analyzed.

Results: Anomalous origin and course of coronary artery were detected in 47 (0.49%) of 9572 patients. The anomalous origins of Circumflex Artery from the RCA or the right sinus of Valsalva are most frequently visualized ( 15 pts [31.9%] ). High taking off of RCA observed in 11 pts ( 23.4% ).The RCA rising from the left sinus of Valsalva were seen in 8 pts ( 17% ).The Left Coronary Artery originates from the right sinus of Valsalva in 5 pts ( 10,6% ).The RCA arising from the LAD in 2pts (4,2% ).Absent RCA in 2 case (4.2%) and single coronary artery from LSV in one case (2.1%). The LCA rising from the Pulmonary Artery ( ALCAPA) in 2 cases and The RCA originating from the PA in one case ( RCAPA ).

Conclusion: Anomalies of coronary artery origin and course are rare but the diagnosis is very important to prevent SCD in young patients. MDCT with the Volume Rendered Images is the non-invasive modality that provides the valuable information to detect these anomalies.

Keywords: Multidetector Computed Tomography; Anomalies of coronary origin and course; sinus of Valsalva

Coronary artery anomalies are a diverse group of congenital heart diseases with manifestations and pathological mechanisms are highly variable. Coronary anomalies include anomalies of origin and course, anomalies of intrinsic coronary arterial anatomy like myocardial bridge, anatomy of coronary termination as coronary artery fistula and anomalous anastomotic vessels. Anomalies of coronary origin and course may associated with arrhythmias, myocardial infarction and sudden cardiac deaths in young people, especially on effort like athletes. We study 9572 patients with coronary MDCT-angiography to evaluate the type and the incidence of coronary anomalies of origin and course[1,2].

All patients who underwent coronary CT-angiography by MDCT 64O Aquilion Toshiba equipment ( IV contrast medium, gantry rotation of 0.33 msec, slice thickness 0.5mm ) in MEDIC HCMC Viet Nam, from January 2016 to January 2019 were included. The main indications of CT-angiography were acute coronary syndrome, stable angina, coronary CT-angiography prior to surgery, congenital heart diseases involving coronary artery...

The CT-angiograms with coronary anomalies were selected and analyzed. The anomalies of coronary origin and course were assessed [3-5].

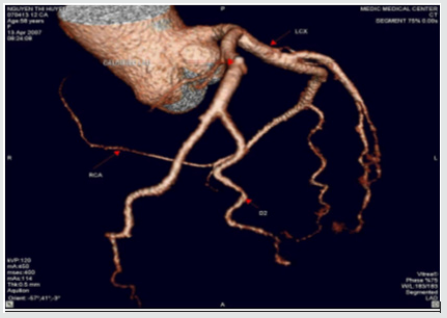
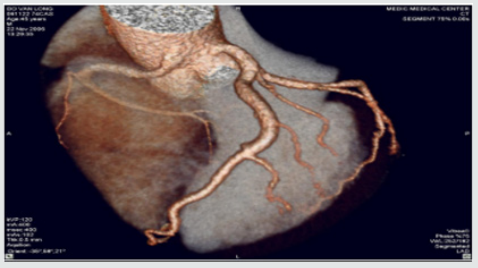
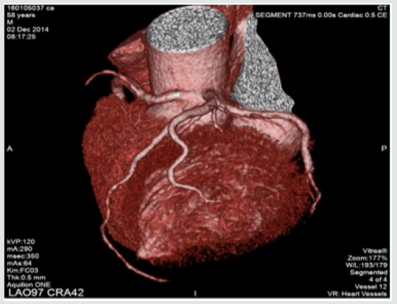
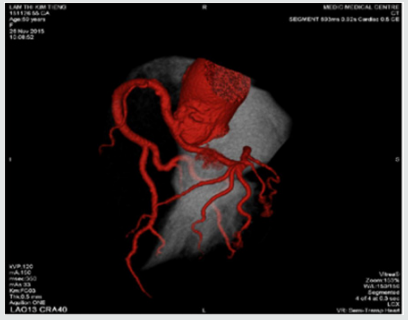
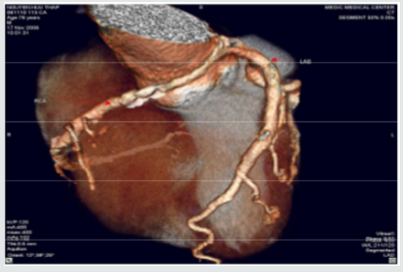
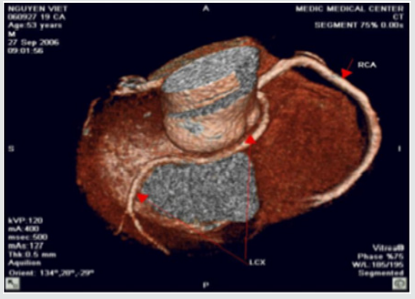
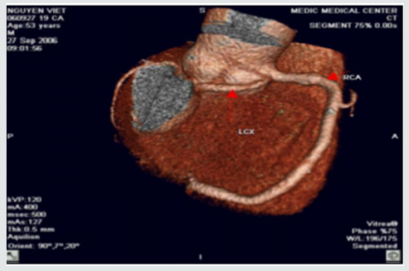
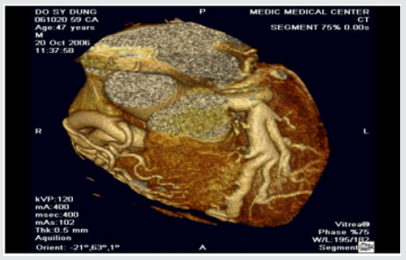
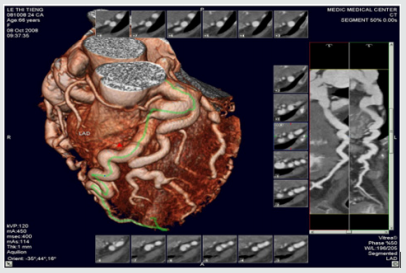
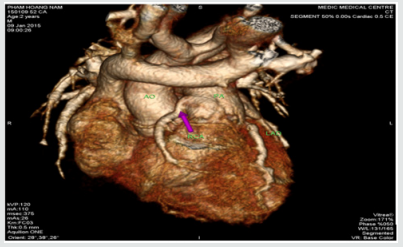
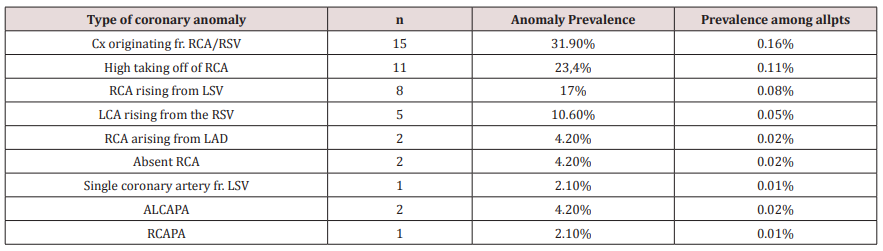
We included 9572 pts with anomalies of coronary origin and course based on results of CT-angiograms that were interpreted by two cardiologists. Anomalous origin and course of coronary artery were detected in 47 ( 0,49 %) of 9572 patients. The mean age of these pts was 63± 8.4, M/F=1.8 . The anomalous origins of Circumflex Artery from the RCA or the right sinus of Valsalva are most frequently visualized ( 15 pts [31.9%] ).High taking off of RCA observed in 11 pts ( 23.4% ) The RCA rising from the left sinus of Valsalva were seen in 8 pts ( 17% ).The Left Coronary Artery originates from the right sinus of Valsalva in 5 pts ( 10.6% ), in this subgroup, a patient presented by myocardial infarction resulting cardiac arrest was notified, the surgical re-implantation of LCA was performed .The RCA arising from the LAD in 2pts (4,2% ). Absent RCA in 2 case (4.2%) and single coronary artery from LSV in one case ( 2.1% ) (Table1 ).The Left Coronary Artery arising from the Pulmonary Artery ( ALCAPA ) in 2 cases ( 4.2% ) and The RCA originating from the PA ( RCAPA ) in one case ( 2.1% ). sinus of Valsalva (Figures 1-10).

Table 1.


Lupinepublishers-openaccess-cardiology

RSV: Right sinus of Valsalva, LSV: Left sinus of Valsalva, ALCAPA: Anomalous Left Coronary Artery from The Pulmonary Artery, RCAPA: Anomalous Origin of the Right Coronary Artery off The Pulmonary Artery.

Figure 1: Single coronary artery rising from LSV.


Lupinepublishers-openaccess-cardiology

This patient is of 52 ages, presented by atypical chest pain, the single coronary artery originating from LSV. The other case report of Prashanth Panduranga revealed the single coronary artery arising from RSV with exertional angina

Figure 2: High taking off of RCA.


Lupinepublishers-openaccess-cardiology

Some time causes myocardial infarction due to excessive angulation between RCA and Aorta. We have in our study one young patient of 24 y.o that had been transferred to the hospital by cardiac arrest , related to this anomaly. Operative re-implanted had been indicated to save the patient

Figure 3: RCA originates from LSV with intra-arterial course resulting Angina


Lupinepublishers-openaccess-cardiology

Figure 4: Anomalous origin of LCA from RSV


Lupinepublishers-openaccess-cardiology

Figure 5: RCA rising from LSV and Intra-arterial course of RCA.


Lupinepublishers-openaccess-cardiology

Figure 6:LCx arising from the RVS and Retro Aortic Course of LCx.


Lupinepublishers-openaccess-cardiology

Figure 7: LCx arising from the RVS and Retro Aortic Course of LCx.


Lupinepublishers-openaccess-cardiology

Figure 8: Anomalous Left Coronary Artery from The Pulmonary Artery.


Lupinepublishers-openaccess-cardiology

Figure 9: Other case of ALCAPA.


Lupinepublishers-openaccess-cardiology

Figure 10: Anomalous Origin of the Right Coronary Artery off The Pulmonary Artery.


Lupinepublishers-openaccess-cardiology
In our study, coronary anomalies of origin and course were detected in 47 of 9572 patients ( 0,49% ) that is consistent with the incidence of 0.27% to 1.66% reported in other series. The most frequent anomaly of origin and course was the Cx Artery arising from RCA/RSV ( 31.9% of anomaly prevalence and 0.16% among all patients ), this incidence is lower than previous published studies. The anomalies of origin and course of RCA were found in 17% and 4.2% respectively from LSV and LAD. This incidence is lower in comparison with previous study. Sudden deaths, myocardial infarction, arrhythmias related to the coronary anomalies were reported previously [6,7]. But these anomalies often asymptomatic, so early detection of coronary anomalies of origin and course is highly important. The former studies mainly based on the result of coronary angiography that is invasive modality. This study demonstrates MDCT is the noninvasive modality that provides important information related to coronary anatomy. Currently MDCT and MRI become fundamental to detection and diagnosis of coronary anomalies. Contrast enhanced ECG-gated 640-row MDCT coronary angiography is an accurate diagnostic method that can precisely detect the coronary anomalies of origin and course


For more Lupine Publishers Social Bookmarking Click on Below link

https://issuu.com/lupinepublishers-oaj/docs/lupine_publishers_social_bookmarking_sites.docx

Thursday, November 5, 2020

Lupine Publishers | Msct In Diagnosis of Congenital Heart Diseases in Viet Nam

Lupine Publishers | Advancements in Cardiology Research & Reports


Background: Congenital heart diseases associated with more malformations, complex aortopulmonary collaterals and anomalous coronary artery. Echocardiography is the initial diagnostic method but this method can be limited in complex congenital heart diseases.

Purpose: To assess the role of MDCT in congenital heart diseases (CHD) diagnosis compare with operative result and interventional angiography.

Methods: 910 patients with congenital heart diseases of 31.000 patients underwent cardiac angiography with 64 and 320 section CT at Medic Medical Center since 09/09/2006 to 30/12/2015.

Results: There are 658 operated cases, most of operated cases demonstrated the exact diagnosis of MDCT in congenital heart diseases.

Conclusions: MDCT is the fast and non-invasive diagnostic method with the high accuracy, overcomes the limit of echocardiography in complex congenital heart diseases diagnosis and provides the panorama and useful information’s prior to the operation.

Keywords: Congenital heart diseases; Cardiac multi-detector computed tomography, Multi-detector computed tomography in congenital heart diseases; Congenital heart diseases computed tomography

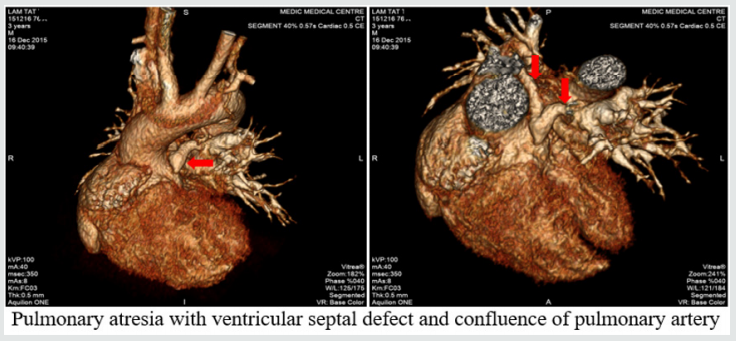
Congenital heart diseases effect ~ 1% of all live births in the general population. Complex congenital heart diseases associated with more malformations, complex aortopulmonary collaterals and anomalous coronary artery. Over the past few decades, the diagnosis and treatment of congenital heart diseases have greatly improved [1-6]. Diagnostic tools: X-ray, ECG, echocardiography, MRI and MDCT. ECG and X-Ray suggest the diagnosis but are not specific. Echocardiography is the initial diagnostic method for patients with suspected CHD but this method can be limited in complex CHD. The great capabilities of MRI for anatomic and functional assessment of the heart but MRI is time-consuming and may require patient sedation. Now enable CT to be used as an accurate noninvasive clinical instrument that is fast replacing invasive cine-angiography in the evaluation of CHD [1,2,5].

I. Improves both spatial and temporal resolution.

II. Increases scanning speed.

III. Improves diagnostic image quality by reducing respiratory artifacts

To assess the role of MDCT in congenital heart diseases (CHD) diagnosis compare with operative result and interventional angiography.

Subject: 910 patients with congenital heart diseases of 31.000 patients underwent cardiac angiography with 64 and 640 section CT at Medic Medical Center since 09/09/2006 to 30/12/2015.

Means and scanning techniques

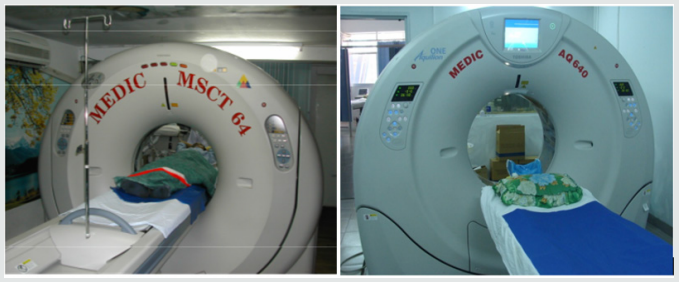
a) Medic Medical Center scanned cardiac CT by 64 MDCT Toshiba Aquilion machine and Toshiba Aquilion One (320 MDCT), 0.5mm slice thickness, 0.5mm imaging reconstruction.

b) Two phases scanning: Don’t inject phase and contrast media injection phase: +Phase doesn’t inject contrast which help locate and assess coronary artery calcification.

c) +Phase inject contrast media: Medicine chasing phase and water chasing phase.

d) Contrast pumping machine is double-barreled Stellant (Medrad).

e) To inject contrast by intravenous right hand.

f) Contrast dose used 1mL/ kg.

g) Drug pump speed depends on patient status and disease.

h) Vitrea software: Reconstructed images by MPR, MIP and VRT.

i) Effective radiation dose is low (320-MDCT is 3.69±061mSv; 64-MDCT is 12-14mSv) (Figures 1).

Figure 1.


Lupinepublishers-openaccess-cardiology

a. The prospective study and case series report compare with operative and interventional angiography.

b. Data collection at the HCM city Heart Institute, Tam Duc Heart Hospital and Medic medical center (Figures 2-17).

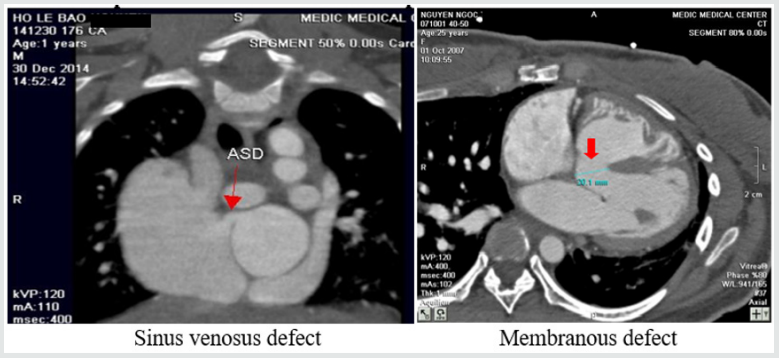
Figure 2: Atrial septal defects and Ventricular septal defects.


Lupinepublishers-openaccess-cardiology

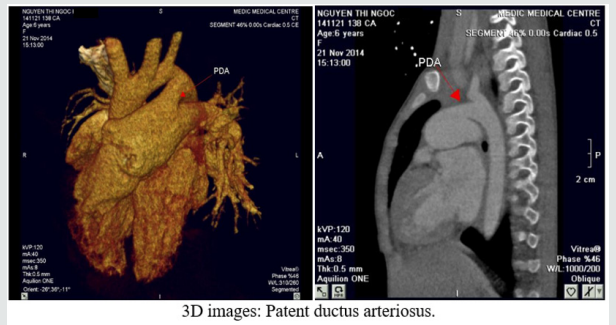
Figure 3: Patent ductus arteriosus.


Lupinepublishers-openaccess-cardiology

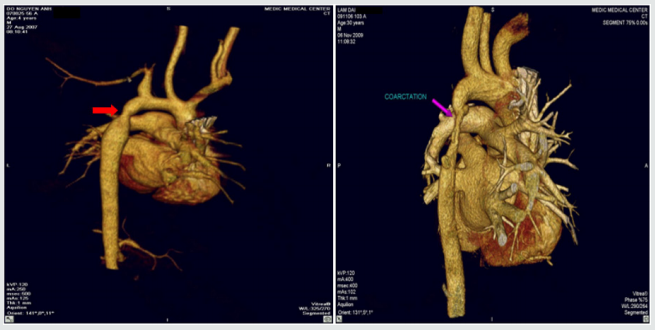
Figure 4: Coarctation of aorta.


Lupinepublishers-openaccess-cardiology

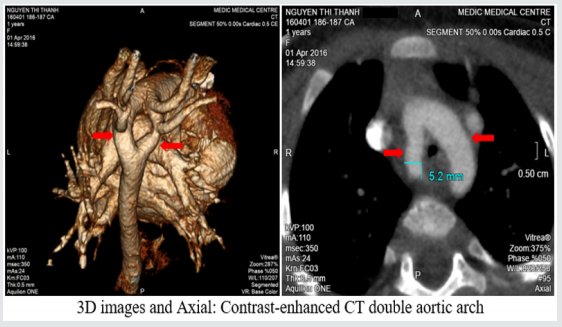
Figure 5: Double aortic arch.


Lupinepublishers-openaccess-cardiology

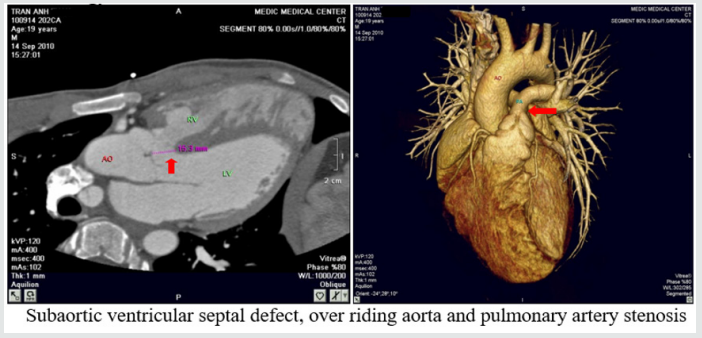
Figure 6: Tetralogy of Fallot.


Lupinepublishers-openaccess-cardiology

Figure 7: Pulmonary atresia with ventricular septal defect.


Lupinepublishers-openaccess-cardiology

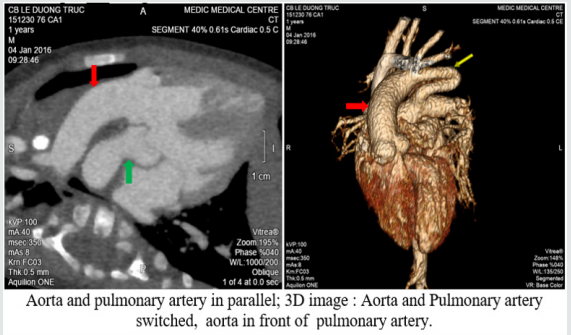
Figure 8: Transposition of great vessels.


Lupinepublishers-openaccess-cardiology

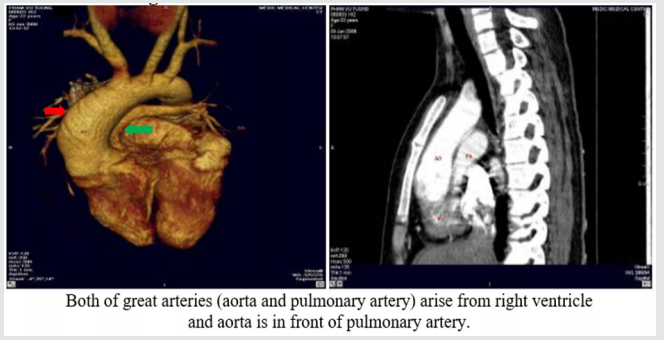
Figure 9: Double outlet right ventricle.


Lupinepublishers-openaccess-cardiology

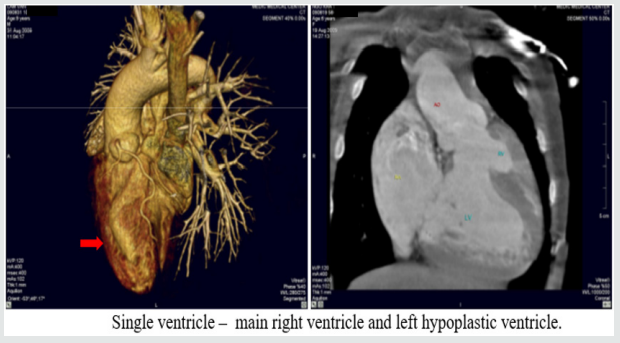
Figure 10: Single ventricle.


Lupinepublishers-openaccess-cardiology

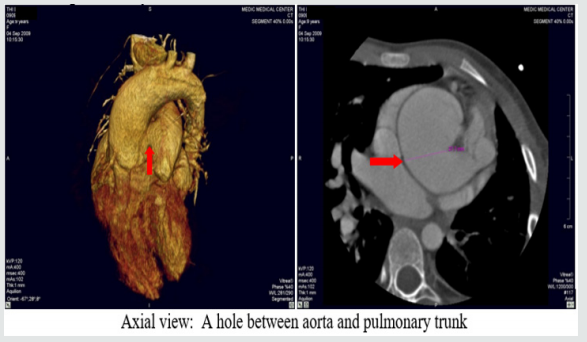
Figure 11: Aortopulmonary window:


Lupinepublishers-openaccess-cardiology

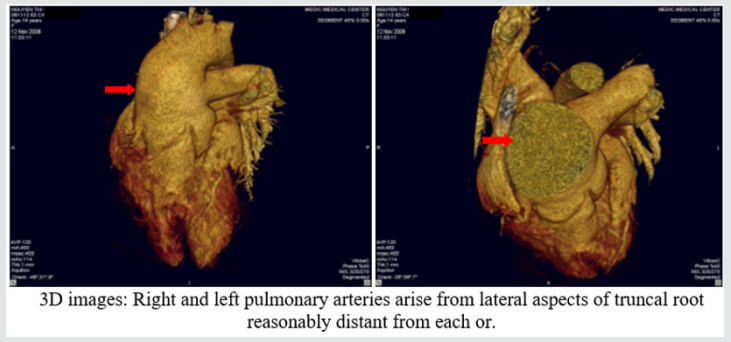
Figure 12: Truncus arteriosus.


Lupinepublishers-openaccess-cardiology

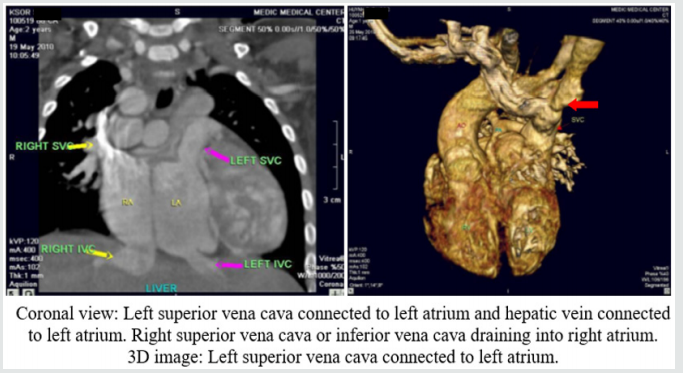
Figure 13: Anomalous systemic venous return.


Lupinepublishers-openaccess-cardiology

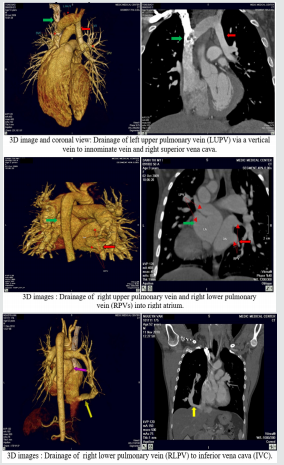
Figure 14: Anomalous pulmonary venous connection.


Lupinepublishers-openaccess-cardiology

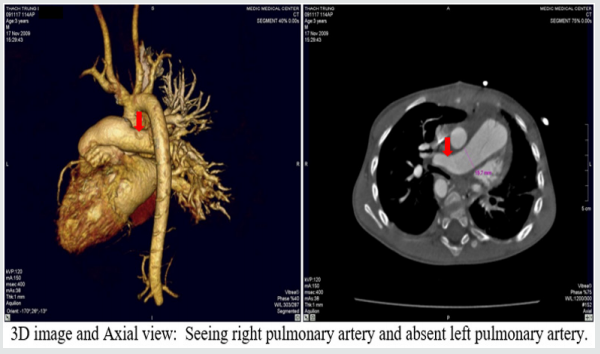
Figure 15: Single pulmonary artery.


Lupinepublishers-openaccess-cardiology

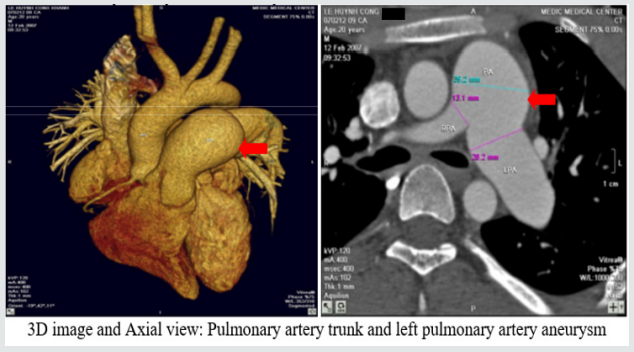
Figure 16: Pulmonary artery trunk aneurysm:


Lupinepublishers-openaccess-cardiology

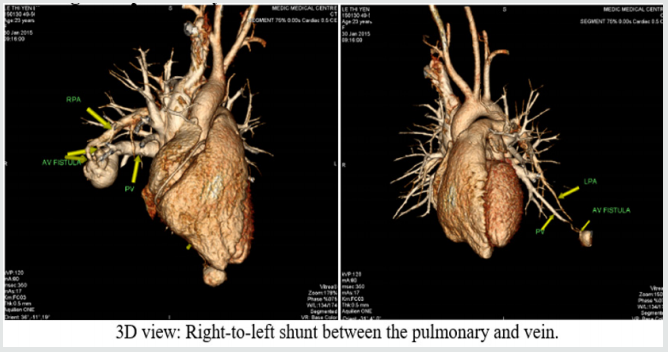
Figure 17: Congenital pulmonary arteriovenous malformation.


Lupinepublishers-openaccess-cardiology

There are 658 operated cases, most of operated cases demonstrated the exact diagnosis of MDCT in congenital heart diseases.

Congenital heart diseases associated with more malformations, complex aortopulmonary collaterals and anomalous coronary artery. Echocardiography is the initial evaluative method for preand post-operation congenital heart diseases but this method can be limited in complex cases. Multi-detector computed tomography overcomes the limit of Echocardiography by multiplanar reconstruction (MPR) and volume rendered techniques (VRT) reconstruction . Volume rendered techniques (VRT) reconstruction clearly demonstrates the relationship between the heart and great vessels.

Multi-detector computed tomography is the fast and noninvasive diagnostic method with the high accuracy. Overcomes the limit of Echocardiography in complex congenital heart diseases. Provides the panorama and useful information’s prior to the surgery.

For more Lupine Publishers Social Bookmarking Click on Below link

https://issuu.com/lupinepublishers-oaj/docs/lupine_publishers_social_bookmarking_sites.docx

Friday, October 30, 2020

Lupine Publishers | The Left Common Carotid Artery Rises from the Main Pulmonary Artery

  Lupine Publishers | Advancements in Cardiology Research & Reports


Abstract

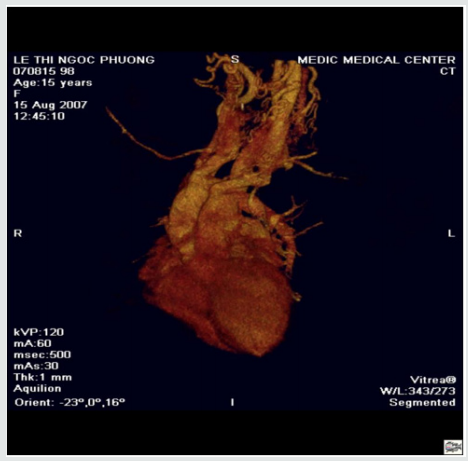
A young female patient of 15y.o presented at my hospital by dyspnea on effort and palpitation for one year. Mental deficiency was notified. Physical examination detected a 3/6 continuous murmur at the 2ndRICS. In the past history, PDA had been suspected by her physician, associated with recurrent bronchitis. Trans-thoracic Echocardiography showed an enlarged LV of 57mm with normal EF of 69% , LCA=5mm, RCA=3.5mm at origin, no suspected sign of PDA was seen. Only a continuous flow was visualized in the PA. CT-Angiography with IV contrast medium showed the Left Common Carotid Artery rising from the Pulmonary Artery trunk. PDA was not presented. The Left Common Carotid Artery then was re-implanted into the aortic arch normally with a favorable postoperative progress.

Keywords: Carotid Artery; Pulmonary Artery; Anomalous origin

Anomalous origin of the left common carotid artery is very rare and has been reported previously. We present an operated case of this topic with clinical finding, cardiac ultrasound and MDCT imaging.

Figure 1: Right aortic Arch.


Lupinepublishers-openaccess-cardiology

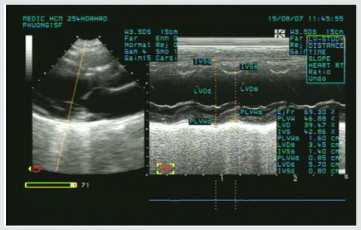
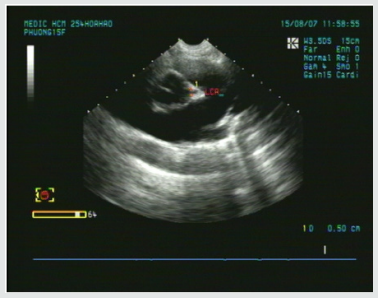
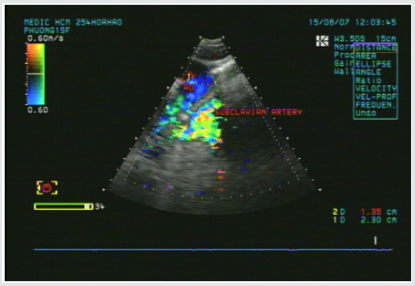
A young female patient of 15y.o presented at my hospital by dyspnea and palpitation when running and fast walking for one year. Mental deficiency was notified, she had some difficulties to learn at school. Physical examination detected a 3/6 continuous murmur at the 2ndRICS. In the past history, PDA has been suspected by her physician, associated with recurrent bronchitis. Her body state was normal with 1m60 of height and 48 kg of weight. She was evaluated immediately by a chest X ray that showed a right aortic arch (Figure 1). The trans-thoracic echocardiography that revealed an enlarged LV of 57mm with normal EF of 69% (Figure 2), LCA=5mm, RCA=3.5mm at origin (Figure 3). No suspected sign of PDA was detected except a continuous flow presented in the Pulmonary Artery (Figure 4).

Figure 2: Enlarged LV& normal systolic function.


Lupinepublishers-openaccess-cardiology

Figure 3: Normal LCA at origin.


Lupinepublishers-openaccess-cardiology

Figure 4: Continuous flow in the PA.


Lupinepublishers-openaccess-cardiology

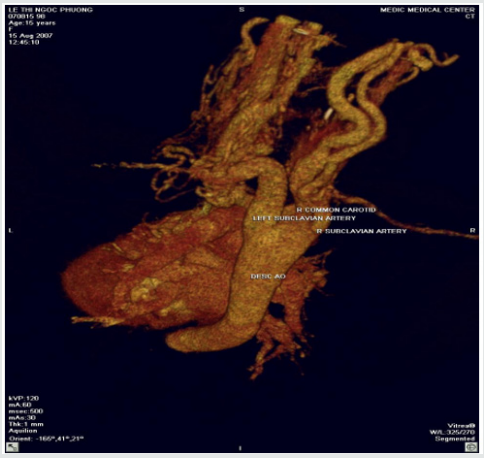
Figure 5: Absence of aortic origin of the LCCA.


Lupinepublishers-openaccess-cardiology

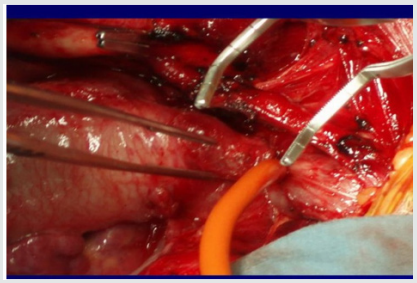
CT-Angiography (MDCT 64) with IV contrast medium Ultravist, slice thickness=1mm visualized a right aortic arch, aberrant origin of the left subclavian artery, dilatation of the branches rising from aortic arch with increased collateral vessels (Figure 5). Especially, MDCT 64 showed the Left Common Carotid Artery ( LCCA ) rose from the PA trunk (Figure 6) PDA was not detected. Patient underwent uncomplicated surgical repair: the Left Common Carotid Artery was re-implanted into the aortic arch normally with a favorable post-operative progress (Figure 7).

Figure 6: The LCCA rising from the Main PA roof.


Lupinepublishers-openaccess-cardiology

Figure 7: Re-implantation of the LCCA.


Lupinepublishers-openaccess-cardiology

Anomalous origin of the Left Common Carotid Artery from the Pulmonary Artery Trunk has been previously reported as rare cases. Kagami Mijaji et al. [1] has reported a case of anomalous origin of the Artery from the Right Pulmonary Artery. Onyekachukwu et al. [2] has described a case of anomalous origin of the Left Common Carotid Artery from the Main Pulmonary Artery. In this article, my patient was not infant with CHARGES syndrome that includes multiple congenital anomalies like the patients in their reports. She was a teenage patient without other congenital disease. The role of ultrasound is orienting for the indication of Computed Tomography or DSA. In case of present turbulent flow in the PA, Coronary Fistula and other shunts from the head and neck vessels should be considered [3].

Anomalous origin of the Left Common Carotid Artery is very rare congenital defect that maybe isolated or associated with some syndromes. Noninvasive diagnostic methods as Ultrasound and CTA may confirm the diagnosis and inform the anatomical relation of the anomalous vessels prior to operate


For more Lupine Publishers Social Bookmarking Click on Below link

https://issuu.com/lupinepublishers-oaj/docs/lupine_publishers_social_bookmarking_sites.docx

Wednesday, October 21, 2020

Lupine Publishers | Platelets and Patent Ductus Arteriosus: Is there a Any Association Really?

 Lupine Publishers | Journal of Cardiology & Clinical Research


Introduction: A great number of the studies have shown that platelets play a role in closure of the PDA. However, studies that reported that platelet parameters were not associated with PDA were also published. We also wanted to contribute to clarify the relationship between PDA and platelet parameters.

Materials and Methods: Preterm infants that less than 34 gestational weeks were examined to echocardiography at the time of detected clinical findings or within 24-72 h after admission to our unit, routinely. The patients were divided into two groups according to echocardiography findings randomly; hsPDA require ductal closure treatment and non-hsPDA. The platelet count, MPV, PDW, PCT and Platelet Mass Index values of both groups were compared.

Results: There was no difference between the two groups in terms of MPV, Platelet count and Platelet mass index. However, PDW and PCT were statistically significantly in the study group than the control group.

Discussion: As a result, according to our study, platelet count, MPV and platelet mass index cannot be used to predict either hsPDA or treatment success, but a low PCT and high PDW can be used predict hsPDA but not treatment success.

Patent Ductus Arteriosus (PDA) can cause mortality and morbidity such as respiratory distress syndrome (RDS), pulmonary hemorrhage, bronchopulmonary dysplasia (BPD), intraventricular hemorrhage (IVH), necrotizing enterocolitis (NEC), retinopathy of prematurity (ROP) [1]. For this reason, early diagnosis and treatment of PDA is the most important point. The main diagnostic method of PDA is Doppler echocardiography [2]. However, there is no clearly consensus on diagnosis of hemodynamically significant patent ductus arteriosus (hsPDA). Therefore, new diagnostic methods of PDA are needed. A great number of the studies have shown that platelets play a role in closure of the PDA [3-6]. The first of these studies, Echtler et al. studied the relationship between ductal closure and platelet parameters in animals [3]. In the same study, the ductus arteriosus did not close (thus, remained permanently open) in animals in which platelet functions were compromised. After this study, they studied on premature infants about relationship between ductal closure and platelet parameters. According to this study, a low platelet count and a low PDW were risk factors for PDA. However, studies that reported that platelet parameters were not associated with PDA were also published [7-11]. We also wanted to contribute to clarify the relationship between PDA and platelet parameters.

This observational, retrospective cohort study was conducted between August 2017 and 2018. Preterm infants that less than 34 gestational weeks were examined to echocardiography at the time of detected clinical findings or within 24-72 h after admission to our unit, routinely [12]. The patients were divided into two groups according to echocardiography findings randomly; hsPDA require ductal closure treatment and non-hsPDA. hsPDA was defined when at least one of the clinical findings associated with PDA was present: a hyperdynamic precordium; a sustained murmur; tachycardia; hypotension; oliguria; an increased pulse pressure; an increase in ventilation pressure and/or oxygen demand; and at least one echocardiographic finding: ductal diameter ≥1.5mm, left atrium/ aortic root ratio ≥1.5, and/or diastolic flow failure in the abdominal aorta or inverse flow. We applied intravenous or oral ibuprofen to close the hsPDA. Intravenous or oral paracetamol was given in cases who ibuprofen is unsuccessful or contraindicated. After treatment, echocardiography was performed again, and the PDA was classified as open or closed. We excluded those with conditions that might cause inflammation or affect platelet count and/or function (Antenatal steroid use, PPROM, early sepsis, chorioamnionitis, congenital viral infections, preeclampsia), congenital heart disease, pulmonary hypertension, perinatal asphyxia, congenital anomaly, chromosomal anomaly, thrombocytopenia (<50.000/mm3), and lack of data. Written informed consent was obtained from all parents. All echocardiographic examinations were performed by Vivid S6 Echocardiography System fitted with a 10S transducer (General Electric Healthcare, Milwaukee, WI, USA). Blood samples taken from an umbilical venous catheter at between 48-72 hours and 7. day, were collected in ethylenediaminetetraacetic acid-containing tubes and blood counts performed using a Coulter Counter model LH (Coulter Electronics, Hialeah, FL, USA). This yielded the platelet count, MPV, PDW, PCT. The platelet mass index was obtained from the platelet count (103/mm3) and the MPV (fL). We recorded gestational age, birth weight, sex, mode of delivery, Apgar scores (at 1 and 5 min) 48-72 h and 7. day platelet parameters, surfactant requirement, ventilation history, IVH, NEC, ROP, BPD, duration of hospitalization and any death.

Statistical analyses were performed using SPSS for Windows ver. 22.0 (SPSS Inc., Chicago, Illinois). The paired samples t-test and independent samples t-test were used to compare continuous variables. Continuous variables are presented as means ± SDs, and categorical variables are given as frequencies with percentages. A p-value less than 0.05 was considered statistically significant.

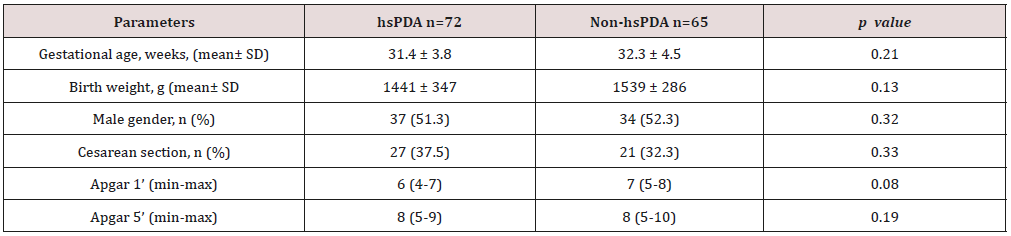
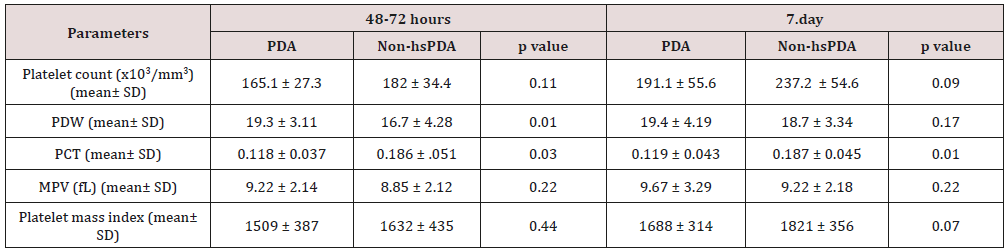
258 newborns under 34 weeks were admitted to our unit, of whom 121 were excluded. The study group consisted of 72 premature infants with hsDPA who applied ductus closure treatment and 65 premature infants without hs DPA or spontaneously closed PDA consisted of the control group (Figure 1). The demographic characteristics of both groups are shown in Table 1. The mean gestational age and the mean birth weight of the study and control groups were, respectively, 31.4±3.8 vs. 32.3±4.5 weeks (p=0.12); 1441±347 vs. 1,539±286g (p=0.08). There was no difference between two groups in perinatal parameters. The platelet parameters of both groups are shown in Table 2. There was no difference between the two groups in terms of MPV, Platelet count and Platelet mass index. However, PDW and PCT were statistically significantly in the study group than the control group.

Table 1: Comparison perinatal characteristics of the study and control groups.

Lupinepublishers-openaccess-cardiology

hsPDA: hemodynamically significant patent ductus arteriosus.

Table 2: Comparison of the platelet parameters of the study and control groups.

Lupinepublishers-openaccess-cardiology

PDW: platelet distribution width; PCT: platocrit; MPV: mean platelet volume; Platelet mass index: the platelet count (103/mm3) X MPV (fL); hsPDA: hemodynamically significant patent ductus arteriosus.

Figure 1: Flowchart of study.


Lupinepublishers-openaccess-cardiology

PPROM: Preterm premature rupture of the membranes; hsPDA: hemodynamically significant patent ductus arteriosus.

Low oxygen pressure, elevated prostaglandin and nitric oxide levels are the main factors affecting continuity of the ductus arteriosus in the uterus. After birth, increased oxygen levels and decreased prostaglandin levels enable functional closure of the DA [13]. In addition to this mechanism, different mechanisms of closure of the ductus began to be discussed. The discussion began when Echtler et al. showed that platelets were attached to the lumen of the closed ductus arteriosus and confirmed this experimental finding via a retrospective study of preterm births [3]. After this animal study, various hypotheses about the role played by platelets in duct closure in newborns have been proposed. The most acceptable hypothesis is an effect of platelets on DA contraction, which occurs immediately after birth in term newborns, triggering hypoxia in the vessel wall by decreasing the blood flow in the venous lumen and vasa vasorum; in preterm newborns, the cells in the ductus wall are fed by the ductal lumen because of the absence of a vasa vasorum. As the ductus wall is thin, contraction is inadequate and endothelial damage and platelet aggregation thus develop because of vesselwall hypoxia. Based on this hypothesis, it was claimed that platelet counts were important in terms of DA closure in preterm infants, as they are in the pathophysiology of adult vascular diseases [14,15]. However, this hypothesis is not supported by the fact that platelet transfusion does not reduce the incidence of PDA in preterm newborns with immune thrombocytopenia and does not increase the PDA frequency in term newborns with severe thrombocytopenia secondary to Wiskott-Aldrich syndrome [16-20].

In Fujioka et al. [21-23]. the platelet count was not related to PDA diagnosis or treatment success. On the other hand, Echtler et al. [3,5,6] reported that a low platelet count increased the hsPDA incidence [24-25]. In some works performed after these contradictory studies, it was reported that large platelets create a greater potential risk of prothrombotic reactions; large platelets are more aggregated than small and normal platelets given the greater number of receptors such as thromboxane A2-B2 and glycoproteins IIb-IIIa on the surfaces of large platelets. It was suggested that the increased metabolic and enzymatic activities of dysfunctional thrombocytes, rather than the platelet count, were associated with PDA [26-29]. We sought to identify parameters related to platelet function associated with PDA. These remain controversial; all of MPV, PDW, PCT, and platelet mass index have been associated with cardiovascular diseases in adults [30-35]. In addition, in a limited number of studies on neonates, the MPV and PDW were shown to be associated with prematurity complications such as RDS and BPD [36-37].

In our study, no difference was found between the platelet counts of the hsPDA and control groups at 48-72 h and 7. day. In addition, there was no difference between the platelet counts of newborn who did and did not fail treatment. In conclusion, the platelet count was not a predictor of hsPDA diagnosis or treatment success. The results of our study contradict those of the two major meta-analyses conducted by Simon et al. and Mitra et al. but support the cohort study of Sallmon et al. [18-20]. PCT was lower and PDW was higher in the study groups than control groups and the difference between the two groups was statistically significant. However, MPV and platelet mass index were similar in both groups. Thus, we conclude that the PCT and PDW can be used to predict hsPDA but not treatment success. Demirel and Dizdar et al. [4]. reported that the PDW was higher in preterm infants with hsPDA than in control groups [38,39]. Bekmez et al [40]. reported that a low PCT increased the hsPDA incidence Demir et al.[41]. found a high MPV and a low platelet mass in the hsPDA group. We also excluded patients who received ibuprofen as ductus closure therapy because of potential effects on platelet count and functions. Infants born to mothers with prior pre-eclampsia, which affects platelet count and ductal flow because of the increased placental resistance, were also excluded [42-44]. We also excluded infants with perinatal asphyxia associated with an increased PDA, thrombocytopenia, and platelet dysfunction [45-47]. Newborns whose mothers had earlier received steroids were excluded because of possible effects on the platelet count. We thus excluded all pathologies that may affect platelet count and function and induce inflammation. There were some limitations of our study. The first limitation of our study is that it was retrospective in nature. The second limitation is modest sample size. As a result, according to our study, platelet count, MPV and platelet mass index cannot be used to predict either hsPDA or treatment success, but a low PCT and high PDW can be used predict hsPDA but not treatment success.


For more Lupine Publishers Social Bookmarking Click on Below link

https://issuu.com/lupinepublishers-oaj/docs/lupine_publishers_social_bookmarking_sites.docx

Monday, September 7, 2020

Lupine Publishers| Variant of Takotsubo Cardiomyopathy with Co-Existent Severe Coronary Artery Disease – A Case Report

 Lupine Publishers | Advancements in Cardiology Research & Reports


TakotSubo Cardio Myopathy (TSCM) is a reversible form of cardiomyopathy characterized by transient left ventricular (LV) systolic dysfunction. Clinically often mimics acute myocardial infarction (AMI) with chest pain or breathlessness with electrocardiographic, cardiac marker(s) and LV wall motion abnormalities. In a third of patients, significant emotional or physical stress precedes the presentation. Often, these patients have normal epicardial coronaries or non-flow obstructive coronary disease. In most patients, LV function shows complete recovery within weeks with favorable outcomes. We report a unique case of TSCM following sudden emotional stress with typical transient apical ballooning; nevertheless, with severe co-existent triple vessel coronary artery disease and complete recovery of cardiac function on medical management.

Keywords: Tako-Tsubo Cardiomyopathy; Apical Ballooning; Coronary Artery Disease

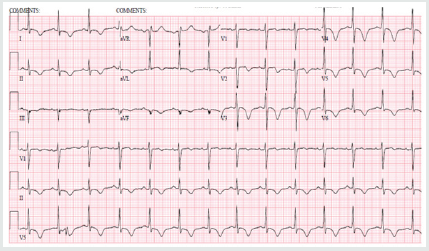
73 year old hypertensive female admitted with sudden onset intermittent chest pains and shortness of breath (< 24 hours after the death of her granddaughters in a road traffic accident). There were no other significant past medical history of note and she never smoked. On arrival, she was tachycardic (heart rate 102) in sinus rhythm, normotensive and clinical examination was unremarkable. Her initial ECG (Figure 1) demonstrated sinus tachycardia with deep T wave inversions in both precordial and limb leads. Her bloods revealed high sensitivity Troponin-T of 395ng/L [normal reference range <15ng/L]. Her bedside echocardiogram revealed typical pattern of “apical ballooning” with severe hypokinesis in the anterior, lateral, septal and inferior walls of the left ventricle, sparing the basal walls. Her left ventricular systolic function was moderately impaired with an ejection fraction (EF) of 40% (Figure 2). Both her clinical presentation and echocardiographic appearances were highly suggestive of “Takotsubo Cardiomyopathy”. Nevertheless, she was conventionally treated for presumed “Non-ST elevation myocardial infarction (NSTEMI)” at the initial stages [1].

Figure 1: ECG on admission showing sinus rhythm with deep T-wave inversions in both precordial and limb leads.


Lupinepublishers-openaccess-cardiology

Figure 2: 2-D Transthoracic echocardiogram (apical view) revealing typical apical ballooning with akinetic apical wall and preserved basal contraction of left ventricle.


Lupinepublishers-openaccess-cardiology

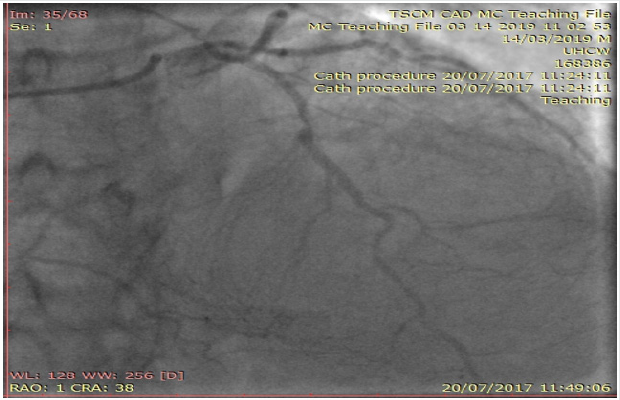
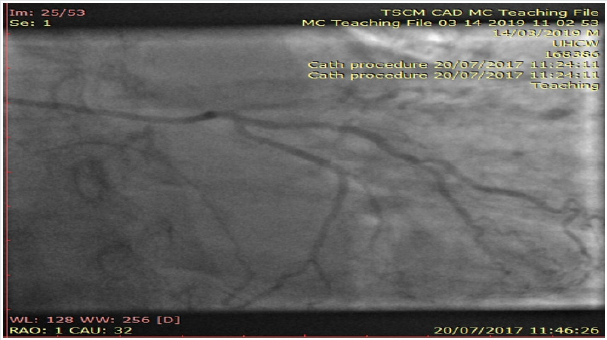
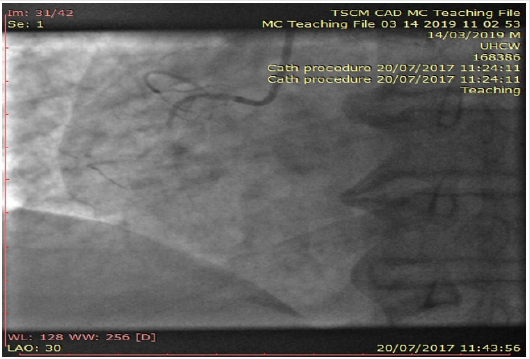
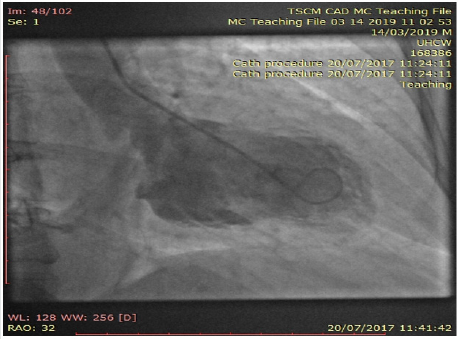
Interestingly, her inpatient coronary angiogram revealed severe triple vessel coronary artery disease (CAD). This was evident by the presence of mild disease in the left main stem, severe mid vessel calcific LAD lesion, severe obtuse marginal (OM1) disease (Figure 3) and chronic total occlusion of her mid right coronary artery (Figures 4a & 4b). However, her distal RCA appears well collateralized from contralateral LC system. The left ventriculogram revealed moderately impaired systolic function with moderate mid to apical anterior and inferior wall hypokinesis, sparing the basal segments consistent with “apical ballooning”. Figure 5, LV in systole] Given her clinical presentation (albeit coronary artery disease and LV dysfunction), multidisciplinary consensus favored medical management as NSTEMI. Expectedly patient agreed and preferred this option too. She was discharged on appropriate treatment and secondary prevention. Interestingly, her Cardiac MRI (CMR) scan at 1-month post discharge showed near normalization of LV function with calculated EF 50% with no evidence of infarction or myocardial oedema or fibrosis. Thence, improvement in her LV function with no evidence of infarction on CMR confirms the diagnosis of Takotsubo Cardiomyopathy, despite her significant CAD. At 12-month follow up, patient still remains stable and symptom free; therefore, with plans to consider surgical coronary revascularization, if worsening symptoms on top of medical therapy [2,3].

Figure 3: Coronary angiogram of left system revealing severe mid calcific left anterior descending artery disease with contralateral collaterals to distal right coronary artery.


Lupinepublishers-openaccess-cardiology

Figure 4a: Coronary angiogram of left system showing severe branch vessel disease in obtuse marginal branch of left circumflex artery.


Lupinepublishers-openaccess-cardiology

Figure 4b: Angiogram of right coronary artery showing chronic total occlusion at the proximal segment.


Lupinepublishers-openaccess-cardiology

Figure 5: Left ventriculogram at systole confirming the typical pattern of “apical ballooning” sparring the basal anterior and inferior segments.


Lupinepublishers-openaccess-cardiology

With her established macrovascular risk factors for CAD (hypertension and age) and clinical presentation together with abnormalities in ECG, cardiac enzymes and echocardiogram, the working differential diagnoses were:

a. Acute Coronary Syndrome (ACS) i.e., Non-ST elevation myocardial infarction

b. TakotSubo Cardiomyopathy or transient apical ballooning syndrome or stress induced cardiomyopathy or broken heart syndrome.

Conventional electrocardiogram (ECG) still remains a costeffective important tool in the assessment of CAD. Nevertheless, its low sensitivity (<50%) and specificity (<80%) in predicting coronary disease still remains a major limitation. Clinicians mostly rely on surface ECGs to localize ischaemic myocardial territory (highly specific) prior to coronary revascularization of the culprit vessel(s) routinely in ACS patients. Clinically TSCM (typical LV appearance of Japanese “Octopus trap” with apical ballooning) often mimics AMI (chest pains, elevated cardiac enzymes and ECG changes) and is characterized by a transient left ventricular dysfunction. Though its incidence and prevalence doesn’t appear to have vastly changed over the years; however clinicians are more comfortable in diagnosing TSCM with better access to imaging (echocardiogram, Cardiac MRI) and invasive investigations (coronary angiogram) nowadays. The Revised Mayo Clinic Criteria suggested the presence of the following to confirm the diagnosis of TSCM [4,5].

a. Transient hypokinesis, akinesis or dyskinesis of the left ventricular mid segments with or without apical involvement– distinctively the extent of regional wall motion abnormalities observed will be beyond the distribution of single epicardial coronary vessel and with often a stressful trigger (but not always present).
b. Absence of obstructive coronary artery disease or angiographic evidence of plaque rupture
c. New electrocardiographic abnormalities or modest elevation in cardiac Troponin
d. Absence of pheochromocytoma and myocarditis.

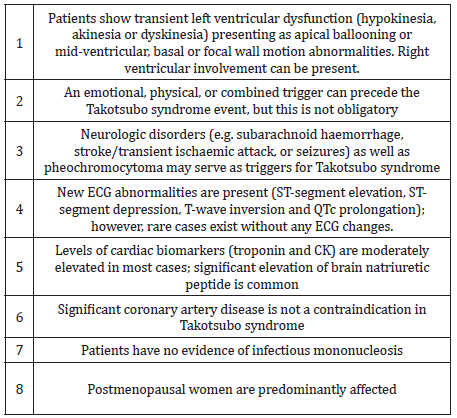
However, concomitant coronary artery disease (CAD) has been reported in 10 – 29% of patients who have been diagnosed with TSCM. In the International Takotsubo Registry (n=1750) 15.3% had some degree of coronary artery disease, although the extent of coronary artery involvement was not discussed in TSCM patients. The new Inter TAK diagnostic criteria highlight the clinical entity that TSCM can exist with concomitant CAD too (Table 1). Our patient meets with these diagnostic criteria for “Takotsubo Cardiomyopathy” together confirming that there was no evidence of infarction in her Cardiac MRI (no sub-endocardial late gadolinium enhancement in her LV or microvascular oedema) as well as complete recovery of her LV function rather than the initially presumed diagnosis of ACS [6].

Table 1: International Takotsubo Diagnostic Criteria (8).


Lupinepublishers-openaccess-cardiology

The pathophysiology for the condition is not well completely understood yet; nonetheless, stress related acute catecholaminergic surge, multi-vessel epicardial coronary spasm, micro-vascular dysfunction, abnormal fatty acid metabolism, myocardial stunning, micro-infarction, direct catecholamine toxicity to myocytes and possible reperfusion injury were proposed as possible mechanisms. On top of the typical transient apical ballooning, other atypical variants including inverted or reversed, mid ventricular or localized have been reported in the literature. In the majority of cases of suspected TSCM, it is appropriate to perform coronary angiography to exclude an acute coronary syndrome given the overlap of symptoms. Also, there is little evidence to support the clinicians in the management of TSCM with co-existent coronary artery disease as highlighted in this case and the clinical dilemma encountered. Therefore, we believe long term follow-up would be really helpful in understanding the disease as well as their management and prognosis for these TSCM patients [7,8].

We report an unusual case of Takotsubo Cardiomyopathy with co-existent severe triple vessel coronary artery disease. This case illustrates the importance of good history taking and the judicious use of diagnostic imaging to arrive at a prompt diagnosis and appropriate management. With limited evidence in literature to support clinicians as how best to manage these patients with severe coronary artery disease with Takotsubo Cardiomyopathy, we highlight the need for International registries with long term follow-ups.

For more Lupine Publishers Social Bookmarking Click on Below link

https://issuu.com/lupinepublishers-oaj/docs/lupine_publishers_social_bookmarking_sites.docx
  

Tuesday, March 3, 2020

Lupine Publishers | Peer Review of Statistics in Surgical Research: Identify The X-Factor or Toss a Coin!


Opinion


Professor Peter Bacchetti’s excellent article [1], highlighting “the other problem of peer review of finding flaws that are not really there based on unfounded statistical criticism, and its demoralizing effect on authors”. I wish to add some thoughts to the debated issues. Professor David Horrobin’s original classics on the subject [2,3]. have not yet been surpassed. It was updated recently [4] and prompted some contributory thoughts [5]. Having enough experience as author of reject articles and some as peer reviewer, I find the most devastating effect to author’s morale is making no comment, giving no reason for rejection or not replying all. The BMJ is guilty on this account as an article of mine was rejected that was accepted elsewhere after minor editing [6]. The BMJ, however, is in the good company of most biomedical journals who apply the COPE rules. The article lacked statistics of any kind that perhaps might be one of the reasons it was disliked at BMJ. To Editors’ credit, however, it took about a month to say ‘No’ that caused no momentum loss, unlike other Journals who reach the same verdict on other articles after 6 months or a year that drag another year or two before the author could recover and gather enough time, interest and energy to face the damn thing again. One subtle aim of that article [6], mentioned to BMJ Editors, was an attempt to say that “there is science and in particular evidence based medicine without statistics”.
It is a devil’s advocate to say statistics has not only been made into a “big lie” but also ‘false God’. It was invented elsewhere but currently worshiped only at most medical and surgical journals. A look at Science and Nature testifies such prestigious magazines have reduced statistics to real size and value as a “tool for testing a hypothesis”. It is not too basic a question for every biomedical peer reviewer to find out the exact role, aim and limitations of statistics. Some was mentioned in an article [7], nobody noticed save the late great Professor GD Chisholm editor of Br J Urology. It was based on a study that was rejected by a grant committee. It aimed at resolving 2 of the most serious puzzles of current clinical practice, postoperative hyponatraemia and the multiple vital organ dysfunction or failure syndrome [8]. However, giving data and statistics [7,8]. before clarifying the theories [9]. has proved as wrong as putting the cart in front of the horse. Einstein’s methods on proposing the special and general relativity theory is the correct way. When statistics was haled in the sixties everyone thought it was the only mean to discover “The Unifying Theory”.
This has proved both immensely costly and wrong. The basic fact is ‘statistics cannot, was not intended to and will never could, make a discovery’. Observation, mental experiments and the X factor are the only way to make a discovery long before it is verified and proved by practical studies and statistical tests. Before explaining the X-factor please allow me tell a relevant true story that symbolizes the current problem with statistics. Two friends of mine in UK had a disagreement, made a bit on a round of drinks and decided the first person to enter the hospital club will be the judge. Guess who did? I did but having no clue on how to resolve the conflict suggested that a flip of a coin might be the best way. They agreed also to my condition that while head or tail will determine the winner among them, if the coin stood on edge the judge should be the winner of all. It did and I won. Another conflict started on: Who should buy the 3rd round of drinks? Both agreed that it was my turn. I explained that buying the 3rd round will gain good company but lose all winnings, and my turn should be the 5th round! The point is statistics can tell the probability of head or tail and exclude the odd but when evaluating to either 0 or 100% and the truth is known, instead of expiring it generates residual arguments. Professor Richard Smith contributed to this debate by quoting Dr Hedge on Professor Robert Fox’s famous thought that “swabbing the rejects with the accepts does not make a difference.”
He added that perhaps it has already been done at BMJ” and asked “How can you know?” With due respect Sir, I frankly think nobody can. Despite a proven incremental value of an average article it does not make a noticeable difference or great loss to scientific advances. Statistically speaking that means a quality article submitted to BMJ has 50% chance of being accepted or rejected. So, why not save everybody the trouble and toss a coin? Here is where statistics has shot itself in the foot. It gives an average chance to the average and an odd chance to the odd but can’t tell which is important. The odd chance of a tossed coin to stand on edge matches that of a breakthrough scientific or medical article coming an editor or peer reviewer’s way but detecting such article makes all the difference. Some call it a hunch or gut feeling. Others qualify it by the three-pronged tests of quality, relevance and civility. Identifying the “X-factor” that makes such an article stand out is worth all the trouble. I honestly do not know but it is the arresting beauty found in Einstein’s famous papers, Newton’s laws, Mozart’s music and Shakespeare’s writing among many examples that include medicine [2-4]. I wrote 2 articles on such para-scientific para-medical stuff to identify the X-factor, “Rules and lures of the science game” and “The Mozarts of Science” sent to journals nearly two years ago and have not received a reply yet. I think a message of “Ignore the big headed bustard” arrived. Qualified people to find out the X-factor are COPE members. Another question that requires a ‘Yes’ or ‘No’ answer would be: if any of Einstein’s papers is evaluated using the current peer review standard and statistics adopted by most biomedical journals, would it be accepted?


For more Lupine Publishers Open Access Journals Please visit our website 

For more Journal of Cardiology & Clinical Research Please Click Here: 

 
Follow on Twitter   :  https://twitter.com/lupine_online 

Interruption of the Aortic Arch in the Adult and Fulminant Myocarditis: A Strange Presentation

Introduction   53 years old female patient, who presented oppressive precordial pain, radiating to the neck and jaw, for which she went to...